A new report has found many crops are far less nutritious than they once were, so we need to eat more of them. Here is how to get your five portions of fruit and veg a day, easily and affordably – and potentially increase that to ten
When Eva Humphries first started working as a nutritionist, she met a client who had just found out he had high blood pressure and high cholesterol, and was on the verge of type 2 diabetes. He had no idea how to change his diet or lifestyle.
The man broke down and cried for 45 minutes, leaving Humphries with “no idea of what to do”, she says. In the final 15 minutes of the session, scrambling for a quick but helpful message, she finally said: “When you look at a plate of food, can you just make half of it veg for me?”
The vaccine is personalized to a patient’s tumor, and results from the Phase 3 trial are yet another example of the promise of mRNA vaccines in treating cancer.
Oscar Belgal, a Dominican immigrant, was shot in the neck on Oct. 8 and detained at a federal prison. His lawyers had said he needed outside medical care.
Immigration agents descended upon Oscar Belgal, an undocumented Dominican immigrant, as he drove with his son along a strip of small stores in New York on Oct. 8.
Health care costs are climbing, putting new pressure on millions of Americans and raising questions about the coverage they can afford. The challenges extend to Medicare Advantage. In some parts of the country, insurers are pulling out of markets or eliminating plans that many rely on. We hear from seniors struggling to navigate those changes, and Geoff Bennett discusses more with Dan Weissmann.
The flu hospitalization rate in the U.S. is at the highest level for this time of year since the 2010 season, according to an update published Friday from the CDC.
Case filed in 2022 by patient unable to afford medicine leads to cap on drug prices for millions who face ruin if diagnosed
The Indian government has moved to reduce the price of cancer drugs after a retired bank clerk took her case to the supreme court.
From next month, 137 cancer drugs in India will be cheaper as the government tries to tackle the tragedy of poorer patients either forgoing treatment, selling land or falling into debt to meet the high cost of some medicines, which are making large profits for hospitals and pharmacists.
Micrograph of melanoma cancer cells —PansLaos—Getty Images
Moderna and Merck reported on Oct. 22 that a customized cancer vaccine for people with late-stage melanoma can reduce the risk of cancer recurrence or death over two years by 42% compared to current treatment.
The study involved more than 1,130 people with Stage 2B to Stage 4 melanoma, all of whom had their tumors surgically removed. Some were then randomly assigned to have a cancer vaccine custom-made after their tumors had been genetically sequenced. They received that vaccine, called intismeran, once every three weeks for up to nine doses, along with Keytruda, a checkpoint inhibitor, every six weeks for up to nine cycles, for about a year. Others were randomly assigned to receive a placebo vaccine and Keytruda.
Intismeran, developed jointly by Moderna and Merck, represents a new way to harness the immune system in cancer, by training immune cells to recognize 34 specific proteins on tumor cells. The mRNA coding for these proteins, or antigens, are encased in a lipid particle in a similar way to Moderna’s COVID vaccine, which used mRNA from the COVID virus’ spike protein. Using this mRNA approach, once cells start making the foreign proteins coded for by the mRNA, the immune system sees them as intruders and mounts a response against them—and the latest data show that the approach works not just against viral proteins but also against those found on tumors.
Keytruda contributes a key part of the response by removing the brakes that keep immune cells from recognizing and attacking tumor cells because they originate from normal "self" cells.
“I was surprised by the fact that the results replicated the Phase 2 [study] so closely,” says Dr. David Berman, chief development officer at Moderna, referring to an earlier stage study the companies released in June that the combination lowered the risk of cancer returning or death by 49% over five years. That study also reported that the therapy lowered the risk of the cancer spreading to other sites by 59% compared to the checkpoint inhibitor alone. “This Phase 3 [study] included a much broader population, so the hypothesis was that the treatment effect would be harder to see. There was a lot of suspicion going in that these results would not be as good as those in the Phase 2. But the fact that they reproduced almost exactly what we saw initially in the Phase 2 blew my mind.”
The companies report that the effect seems to start six months into the therapy—an important insight in understanding how immune-based approaches may work in cancer. “We think it’s because the immune system takes time to be activated,” says Berman. That includes making sure that immune cells like T cells, which are critical to recognizing and controlling cancer, have time to learn to detect tumors. Berman says these results could also help to explain why only about 30% of cancer patients respond to the checkpoint inhibitors, a powerful new tool in cancer that allows immune cells to see tumors rather than thinking they are "self" cells and therefore not foreign. “This shows us that in a significant percentage of patients, the checkpoint inhibitors are not doing anything because the immune system hasn’t even been educated to recognize the cancer cells,” he says of the potential role that the mRNA-based intismeran may play. “That’s where we now need to focus—on how to better educate the immune system. It’s a big leap, a big piece of information, that there is now another way to educate the immune system to recognize cancer.”
Data on overall survival of people on the combination therapy isn’t available yet.
Moderna and Merck are studying the intismeran-Keytruda pairing in other cancer types in nine other studies, such as pancreatic and gastric cancer, as well as in three late-stage trials of non-small cell lung cancer. They are also exploring the role of using intismeran alone in an early study in lung cancer.
Traditionally, personalized therapies have not been practical as medical treatment because of their high cost and long timeline to develop. But Berman is confident that the bespoke process of making an individualized mRNA cancer vaccine for each patient is both scalable and potentially affordable. “We have scaled down the technical footprint and have plans to scale up [the program] to look at different tumors,” he says. “The nice thing about the [mRNA] system is that it’s purely enzymatic, so no cell cultures need to be grown.” Another advantage of using mRNA is its speed—scientists at Moderna can develop a customized vaccine based on a patient’s tumor within weeks—critical for any patient with cancer.
Correction, Oct. 23
The original version of this story misstated the length of time of a study that showed a 49% reduction in recurrence of cancer. It was over five years, not over a year.
Although the case is considered exceptional, investigators are working to determine how the infection occurred and whether the pathogen played a role in the patient’s death.
New Yorkers march in support of universal healthcare this summer. | LightRocket via Getty Images
Americans are furious about the state of our healthcare system.
A recent KFF poll found 60 percent of US adults worry about the cost of medical care — more than gasoline, food and groceries, or their rent or mortgage. One in three Americans say they worry every day or almost every day about their ability to afford healthcare, per a new survey from the Pew Research Center. There seems to be a growing appetite for reform, too: More than 65 percent of Americans say they support the government spending more tax dollars to lower healthcare costs.
Democrats are trying to weaponize those frustrations against the Republicans who currently hold Congress and the White House. By a 2-to-1 margin, voters say they trust Democrats over Republicans on healthcare. That could mean single-payer Medicare-for-all or a new public insurance option or maybe something else. What all this energy leads to will depend on what happens in November. The candidates themselves are framing the stakes in those existential terms.
Sign up for the Good Medicine newsletter
Our political wellness landscape has shifted: new leaders, shady science, contradictory advice, broken trust, and overwhelming systems. How is anyone supposed to make sense of it all? Vox’s senior correspondent Dylan Scott has been on the health beat for a long time, and every week, he’ll wade into sticky debates, answer fair questions, and contextualize what’s happening in American health care policy. Sign up here.
“Medicare for all is where we need to go,” Abdul El-Sayed, the Democratic candidate in the Michigan Senate race whose support for the policy has been widely covered, said during an August interview with CNN. “And my hope is, both coming out of the 2026 midterms and then out of 2028, that we’re going to be on our way to a Senate majority to be able to get this done.”
Real change will have to wait for the 2028 presidential election and a new occupant in the White House. But this year’s midterms are still a make-or-break moment: The candidates who get elected this year, and how they shape the upcoming presidential primary debate and actions in Congress, will determine whether healthcare reform happens at all.
If you’re fed up with the state of American healthcare, and you want to see a change, you should show up for the midterms on Tuesday, November 3.
Big midterm wins can beget big healthcare wins
The classic pattern in American elections is that more voters go to the polls during presidential campaigns than during the midterm elections when only House and Senate seats are on the ballot. Turnout has started to tick up for the midterms in recent years, but it still trails behind presidential years. Midterms suffer from the perception that there’s not as much at stake if the White House is not on the line.
But that’s never been strictly true.
Midterm elections are extraordinarily important in shaping the future of policymaking, even if the payoff is delayed. They help determine both the character of the Congress that could eventually pass a major bill after the next presidential election, and the kind of ideas and policies that are going to be prioritized.
“Voters should see 2026 and 2028 as the elections that will guide the next big change in our healthcare system,” said Natalie Davis, CEO and co-founder of the advocacy group United States of Care, in a statement to Vox. “These elections will be how voters’ demands are heard — and will tell us whether the next real window for change will come with serious reforms or missed opportunity.”
A walk through the recent history of healthcare reform should help make the stakes of the 2026 elections clear.
In 2006, the national mood looked similar to what we’re seeing today. A very unpopular Republican president was in office, and the country had soured on his agenda. George W. Bush’s foreign wars and his misguided attempt to overhaul Social Security gave Democrats an opportunity to win big in the 2006 midterms — and they did. Dems won more than 30 seats and secured a comfortable majority in the House. In the Senate, they won six seats and narrowly took control of that chamber too.
It was a resounding rejection of the Bush administration, and it set up the next decade of Democratic policymaking. At the highest level, the midterms gave energy to the progressive wing of the Democratic Party, united as they were around their opposition to the Iraq War, and that energy carried over to the presidential primary. Barack Obama defeated Hillary Clinton and won the presidency, springboarding off of the excitement that started with the 2006 elections.
Dems’ success in the midterms also helped put lowering healthcare costs at the forefront of the Democratic agenda. That encouraged both Obama and Clinton to develop detailed healthcare policy proposals during their primary campaigns and ultimately set the stage for the Democrats to pursue the Affordable Care Act once they had full control of the government in 2009.
And then there is the literal size of the congressional majorities that parties need to pass their agenda. Voters may not spend much time thinking about whip counts, but one or two elections in a midterm year can ultimately decide the fate of the next president’s agenda.
Part of the reason Democrats were able to pass the ACA was that they built on their huge wins in 2006 with more wins in 2008 and held massive congressional majorities once Obama was sworn in. And once the debate over healthcare reform really got started, they needed every single vote. It was especially important in the Senate: Democrats had exactly 60 votes in 2009. That meant if all of them united together, they could pass filibuster-proof legislation — so long as nobody defected. That was only possible because in 2006 Mark Pryor won a Senate seat in Arkansas, Sherrod Brown triumphed in a Senate race in Ohio, and Jon Tester beat an incumbent Republican in Montana.
Without those wins in 2006, the Democratic legislative agenda in 2009 would probably have looked different. They might’ve had to pursue a more limited healthcare reform plan; maybe the ACA wouldn’t have passed at all.
What kind of Democrats will be on the rise in 2028?
The 2006 midterms both created the opportunity for the ACA — and set the limits on what the legislation could actually achieve. Democrats had that 60-seat Senate majority, but within it were many more moderate members. Policies like the public option (which would have authorized the government to create its own health insurance plan to sell alongside private insurance) couldn’t get sufficient support. That is the dilemma of policymaking: You need those swing-seat members to win, which often means tacking to the center, but you also can’t pass anything they won’t get on board with.
Nevertheless, that is a good kind of political problem to have, one which Democrats would be thrilled to face in January 2029. All of which brings us to 2026. What are we going to do now?
It all starts with the vote count. Most projections expect the Democrats to win between 10 and 20 House seats. But the difference between 10 and 20 could be substantial. The cushier the majority, the further you can push the policy agenda. More than 30 House Democrats actually voted against the ACA, but they could still narrowly pass the bill because of the huge majority that they had started building in 2006.
If you live in one of the districts — like Arizona’s Sixth or Colorado’s Eighth or Florida’s 22nd, to name just a couple of the 21 toss-up races identified by the Cook Political Report this year — that forecasters say is competitive this year, you could have an outsized say in what the future of policymaking looks like. But even in safe districts, you should vote: Elections are the most reliable way we have to gauge public opinion, and strong victories for the candidates who prioritize healthcare send a message.
The same goes for the Senate. If Democrats sweep all of the competitive races, they could have up to 55 seats in the Senate in 2027 — with a chance to build on it in 2028. If you are a voter in Kansas, Michigan, Ohio, Texas, Alaska, Maine, New Hampshire, or Iowa, your ballot carries extra weight for the next steps in US healthcare reform. If the Democrats can reach 60 votes again in 2029, they would have much more flexibility about what to pass. Even if they fall short of that magic number, the more of a cushion they have above 50, the more likely that their Senate leaders can find support for altering Senate rules for the filibuster and get an ambitious bill approved.
How you can get involved this election
If there is ever going to be a path to a true healthcare overhaul, it starts with this year’s elections. If you want to see a change, you can vote — and you can do more than that.
The results of this year’s midterms will also set the terms of the debate among Democrats. We are likely to see “show” bills advanced by Dems next year that may have no chance of being signed by President Donald Trump, but that will give us a sense of what kind of policies the party wants to pursue and how much support there is for them. Believe it or not, the first Medicare prescription drug negotiations bill passed the House in 2007 after Democrats’ big wins in 2006 — even though the policy didn’t become law for another 15 years. The broader public may not pay much attention to this kind of doomed-to-fail legislation, but it is often a window into the future.
“One challenge for Democrats is finding the next big health care idea beyond the Affordable Care Act that will resonate with voters and respond to their affordability concerns,” said Larry Levitt, executive vice president for health policy at KFF. “One big difference between now and 2006 is that back then there was already a lot of coalescing around ideas that ultimately led to the ACA. All the major Democratic candidates for president in 2008 supported something like that. I’m not sure that’s true now, at least not yet.”
Democrats are already aligning on a wide range of healthcare ideas, from reviving the public option to free primary care to the full-blown Medicare-for-all supported by progressive candidates, some of whom are in competitive elections. If El-Sayed wins the Senate race in Michigan, for example, that could supercharge a debate around Medicare-for-all. It could also provide momentum to any progressives who run for president — Alexandria Ocasio-Cortez, to name one obvious example — and decide to make Medicare-for-all a pillar of their platform.
But if El-Sayed and other progressives were to fall short, that could make Democrats more timid about being ambitious in the 2028 campaign and afterward. Still, he’s far from the only candidate in a crucial race to put their support behind Medicare-for-all. There is Randy Villegas in an important California House race. Troy Jackson has bet on it as part of his bid to topple Sen. Susan Collins in Maine. All of these races will send a signal to the party about what the public wants and is willing to turn out for.
In some ways, winning elections is the easy part. Legislating is hard, and any eventual healthcare law will surely involve compromises and unexpected surprises. Who knows what will be happening in the world in 2029?
“The bottom line is: 2026 is a healthcare election,” the leaders of the advocacy group Protect Our Care wrote in a campaign memo this month. “After November, it’s up to Democrats to keep up the fight to deliver relief to families and make healthcare affordable and accessible for every American.”
Microsoft’s new AI diagnostic system beat generalist doctors on hard cases, according to a study in Science. But most of the improvement seems to come from the AI models underneath, not from Microsoft’s system itself.
Amber Kostka, who owns The Stockpot restaurant in Hampton Roads, Va., says she has tried to do right by her employees by offering them health insurance, alongside good wages and a 401k.
But as costs have risen—premiums have roughly tripled since the company first started offering health insurance in 2018—her employees are increasingly telling her they can’t afford health insurance. That’s even though she splits the cost of premiums with employees, which are roughly $400 a month.
Instead, employees are dropping out of the plan and going uninsured, she says. About 35% of her eligible employees now buy the employer-sponsored health insurance, she says, down from 50% prior to COVID. She wants to warn them about the risks of going without insurance, she says, but also knows their finances are extremely tight. “It’s just a cost thing, at the end of the day,” she says. “You can’t stop paying for groceries.”
Her employees aren’t alone. The share of working-age U.S. adults without health insurance rose to 11.2% in 2026, up from 8.9% in 2024, according to new research from the Commonwealth Fund. People don’t have health insurance because the costs of everything—including gasoline, housing, and food—are rising, and they’re deciding they can’t afford to pay for even employer-sponsored plans like Kostka’s. “The whole system just seems like a complete gamble with people’s lives,” she says.
Some people are looking at the price of plans on the Affordable Care Act marketplace and deciding they can’t afford health insurance. Premiums on the ACA marketplaces increased by an average of 58% in 2026 after Congress decided last year not to renew expiring subsidies.
Ironically, these uninsured Americans may be helping drive the cost of health care even higher, fueling a cycle in which health insurance gets more expensive, forcing more people to drop coverage. As hospitals field more uninsured patients, they have to pass the costs of uncompensated care onto someone. “When providers have to provide a lot of uncompensated care, how do they make themselves whole? They raise prices,” says Beth Umland, director of employer research for Marsh, the health benefits consultant company formerly known as Mercer.
Of course, having more uninsured Americans isn’t the only reason costs are rising. A Marsh survey of employers recently found that they expected total health benefit costs per employee to rise 8.2% in 2027, the highest increase since 2003. One reason was that the consolidation of health systems was leading to higher prices, as some systems had monopolies in certain markets. Another was that lower government spending for public health programs was leading to higher costs for private sector plans.
“This is starting to feel—’unsustainable’ is the word you hear,” she says.
Many of the reasons why health care costs are rising may seem minimal until you start adding them up, Umland says. For example, more doctors are using AI scribes in care, which are helping them bill for more services, making care more expensive, she says. A clause of the No Surprises Act, which was passed by Congress in 2020 to protect patients from surprise medical bills but which allows disputes to be settled by arbitration, has also added billions to costs, she says.
There are also increasingly more treatments available for patients, and those treatments are more expensive than the ones they’re replacing, she says. One example: GLP-1s, which may save insurers money in the long run on health costs but which are expensive upfront. “That’s just a whole new category of expense that didn’t exist before,” she says.
In its survey, Marsh found that many employers were planning to pass costs onto employees after years of trying not to do so.
Overall, workers are paying on average about $7,471 annually towards premiums for employer-sponsored family health benefits this year, up 9% from 2025, according to a new employer health benefits survey from KFF. Workers at small firms with less than 200 employees—like Kostka’s—are especially hard hit, paying about $9,687 towards family coverage: $2,847 more than workers in larger firms.
And even as they pay more for health care, the plans available to them are getting costlier to use. The average deductible for employer sponsored plans has increased 34% over the last 10 years, according to KFF.
What employers are doing
Kostka says there have recently been fewer health insurers in her area to choose from. Two years ago, she switched from just buying insurance outright for her employees, which many small businesses do, to self-funding the plan. She was able to do this because her employees are relatively young and healthy, she says, making her risk of incurring big medical costs for cancer or a catastrophic illness relatively low.
But she knows she’s just a major diagnosis away from being dropped from the self-funded plan, she says. “It’s a little bit of a gamble right now,” she says.
There are some things employers can do to push back against high health care costs, says Jim Winkler, chief strategy of the Business Group on Health, which published its own recent survey of employers which projected health care costs to rise 9% in 2027, the highest forecast the group has ever recorded.
Some employers are dropping coverage for GLP-1s for weight loss to save money, he says. Others are trying to drive employees toward what are called Centers of Excellence—essentially hospitals or medical practices with high ratings that may save money in the long-term since employees won’t need to return again and again for care. Some employers are also telling employees to try to find cheap, legitimate medications where they can—from sites like GoodRx, for example—and reimbursing them, rather than getting medications from a pharmacy benefit manager.
“We’re just painting a really challenging picture for health care costs,” he says, “which leads employers down the path of needing to find things to do to take action to mitigate them.”
A small number of employers are deciding not to offer health care at all and are instead offering employees cash to buy their own plans through the ACA marketplace. This option, called an ICHRA (Individual Coverage Health Reimbursement Arrangement) is pushed by Republicans, Winkler says, and was introduced during the first Trump Administration.
Small employers, though, often can only choose from available plans, and if there aren’t many, they don’t have much room to negotiate.
It’s a problem facing Mas Torito, owner of Kokoro restaurant in Denver. He spent close to $150,000 in premium payments for his employees in 2025 and is on track to spend $200,000 in 2026. That’s about 2.7% of revenues; most restaurants only have margins of 2-3%.
“Really since COVID, every single year feels like there are these extra pressures on us,” he says.
Kokoro has been in business for 40 years, and some of Torito’s employees have been working at the restaurant the whole time. He suspects that having an older pool of employees is part of what’s driving his health care costs up every year.
“I think they see the number of claims and costs every year going up,” he says, “and that translates into higher premiums.”
Like Kostka, Torito is committed to offering health insurance for his employees, even as his own costs rise. And like Kostka, he’s hearing from more employees that they can’t afford it. Now, only about 40% of his employees buy the insurance, he says.
“I get it,” he says. “The deductible keeps going up every year, the insurance keeps going up. It’s enough where people are really thinking, ‘Hey, do I want insurance or not?’”
Christina Applegate at the 2023 Screen Actors Guild awards. | Valerie Macon/AFP via Getty Images
Christina Applegate, the actor who has been one of the most visible faces of multiple sclerosis since her 2021 diagnosis, made a stunning revelation this week: She does not have MS after all. And her doctors still don’t know what is causing her debilitating symptoms.
“I’m back at square one,” Applegate told fellow actor Jamie Lynn Sigler, who does have MS, on Sigler’s podcast MeSsy. “I was not happy at all. Everybody else was so happy.”
It is a harrowing predicament for Applegate, and hopefully her medical team is able to get her the diagnosis and treatment she needs. But the fact is, her experience is not unique. Even as more and more Americans get diagnosed with multiple sclerosis, misdiagnosis remains all too common. According to one meta-analysis, roughly 15 percent of MS diagnoses may actually be false positives.
How could such a common medical condition — roughly 1 million Americans are living with the disease, about one in every 350 people — remain such a mystery? After Applegate’s announcement, I called some leading experts on MS to ask why diagnosing the disease is such a challenge, and what they want people to know. Here’s what I learned.
Why MS can be challenging to diagnose
Multiple sclerosis is an autoimmune condition: The body mistakenly attacks cells meant to protect your brain and spinal cord, and the resulting damage interrupts nerve signals and causes the disease’s telltale symptoms of motor impairment, tingling sensations, and vision problems. Some people experience a rollercoaster of relapses and remissions; others see the disease steadily progress, eventually leading to serious disability.
The reality is, scientists still don’t really know what causes MS to develop, said Dr. Andrew Solomon, a neurologist at the University of Vermont who specializes in MS. Smoking is a known risk factor. Obesity and metabolic problems play a role, but we need more research. Even the precise role of genetics remains something of a mystery. “We don’t really know what causes or triggers the autoimmune response in any given individual,” Solomon said.
And that’s where the challenge in diagnosing it begins.
First, the testing can be imprecise; there is not a single test that reliably diagnoses MS. If a doctor suspects their patient may have MS, they usually undergo an MRI, which their physicians then scour for lesions that are typically associated with the disease. But those scans are still subject to interpretation: Other rare conditions sometimes resemble MS in imaging, as can diseases of blood vessels in the brain. You can also receive a spinal fluid analysis to check for abnormalities in your immune system, which the vast majority of MS patients have.
The nature of MS symptoms adds to the difficulty. They can often be vague early on: brain fog or fatigue or a general malaise. The tingling or vision problems can be similar to symptoms for other conditions that are not MS, and they are easily dismissed if they go into temporary remission, as often happens during the initial phases of the disease.
“Neurological symptoms sometimes can be vague — numbness, pins and needles — and it’s usually short-lived,” Dr. Saud Sadiq, chief research scientist and director of the Tisch Multiple Sclerosis Research Center of New York, told me. “Unless they’re taken seriously initially, they may be ignored because by the time the patient goes through the healthcare system and is actually referred to a neurologist, the symptoms have abated.”
If your doctor is diagnosing you with MS, ask directly: What’s the evidence?
“Because it’s so heterogeneous, it doesn’t present in the same way in everybody and can have varying severity, it can be hard to diagnose sometimes,” Solomon said.
Lastly, when people are experiencing debilitating symptoms, there is pressure to deliver some diagnosis — and that may push some doctors to leap to MS even if they are not sure, Solomon said. The recent advent of effective treatments that help manage the disease’s symptoms, especially when it is caught early, may add to that pressure, even if the better course would be to continue monitoring the person before they start a medication.
“There may be a lot of clinicians who, if they can’t find a better explanation than MS, may be inclined to diagnose MS, even if they don’t really meet our diagnostic criteria, because they’re worried about missing a window of opportunity to treat somebody,” Solomon said.
There is reason to hope the MS misdiagnosis problem could get better. The National Multiple Sclerosis Society released new diagnostic criteria in 2024 that Solomon said more physicians should become familiar with to better distinguish MS from problems like migraines or vascular disease. And because imaging is involved in diagnosis, there is optimism that AI could be a powerful new tool in delivering more accurate results.
What everyone should know about MS symptoms and diagnosis
The good news is that MS, when diagnosed properly, is a treatable condition these days. “The prognosis with new drugs is extremely good for long-term care,” Sadiq told me. “If patients stick to treatment at a good MS center, you can look forward to a life without disability in 2026.”
So it is worth being vigilant and talking to your doctor if you experience any concerning symptoms. You should seek care if you have numbness or pins and needles that persists for more than 24 to 48 hours, Sadiq said, or have motor problems, like one hand won’t work as you try to play piano. Dr. Annette Langer-Gould, who develops and evaluates programs for MS care at Kaiser Permanente, said numbness in your abdomen, chest or back, as opposed to your extremities, is a particular cause for concern. If one eye has normal vision and the other is blurred, that’s another good reason to get checked out.
If you do get tested, make sure the actual images of your MRIs end up being reviewed by an expert in MS. “The most common reasons the disease is still misdiagnosed are related to the providers’ lack of expertise usually in reading MRI scans,” Langer-Gould said. The spinal tap may sound scary, and doctors sometimes don’t recommend them because their insurance reimbursement is low — but they add to the confidence of a diagnosis. They are worth it, she said.
“American patients are very afraid of the spinal tap,” Langer-Gould said. “My message to patients is: Listen, just get the spinal. This way we’ll be sure.”
And do not be afraid to seek a second opinion for such a serious diagnosis, Sadiq added. Every state has a recognized MS center. If your doctor is diagnosing you with MS, ask directly: What’s the evidence? If your doctor is recommending that you start treatment, it could also be worth checking whether they have a relationship with a pharmaceutical company that affects how you perceive their judgment, Langer-Gould said.
People who have already been diagnosed may also be shaken by the Applegate news and question whether their own diagnosis might be wrong. Solomon said that folks should have a frank conversation with their physician about how exactly their case met the diagnostic criteria. With proper imaging and the spinal fluid tests, you can get to a confident diagnosis for the vast majority of people. But be your own advocate to make sure you’re satisfied.
“For many people, the diagnosis actually can be very straightforward,” Solomon said. “We really have no question about what it is.”
Immune-based treatments for cancer have become the biggest new advance in tackling tumors, and the latest approval could make a big difference for some people with rectal cancer.
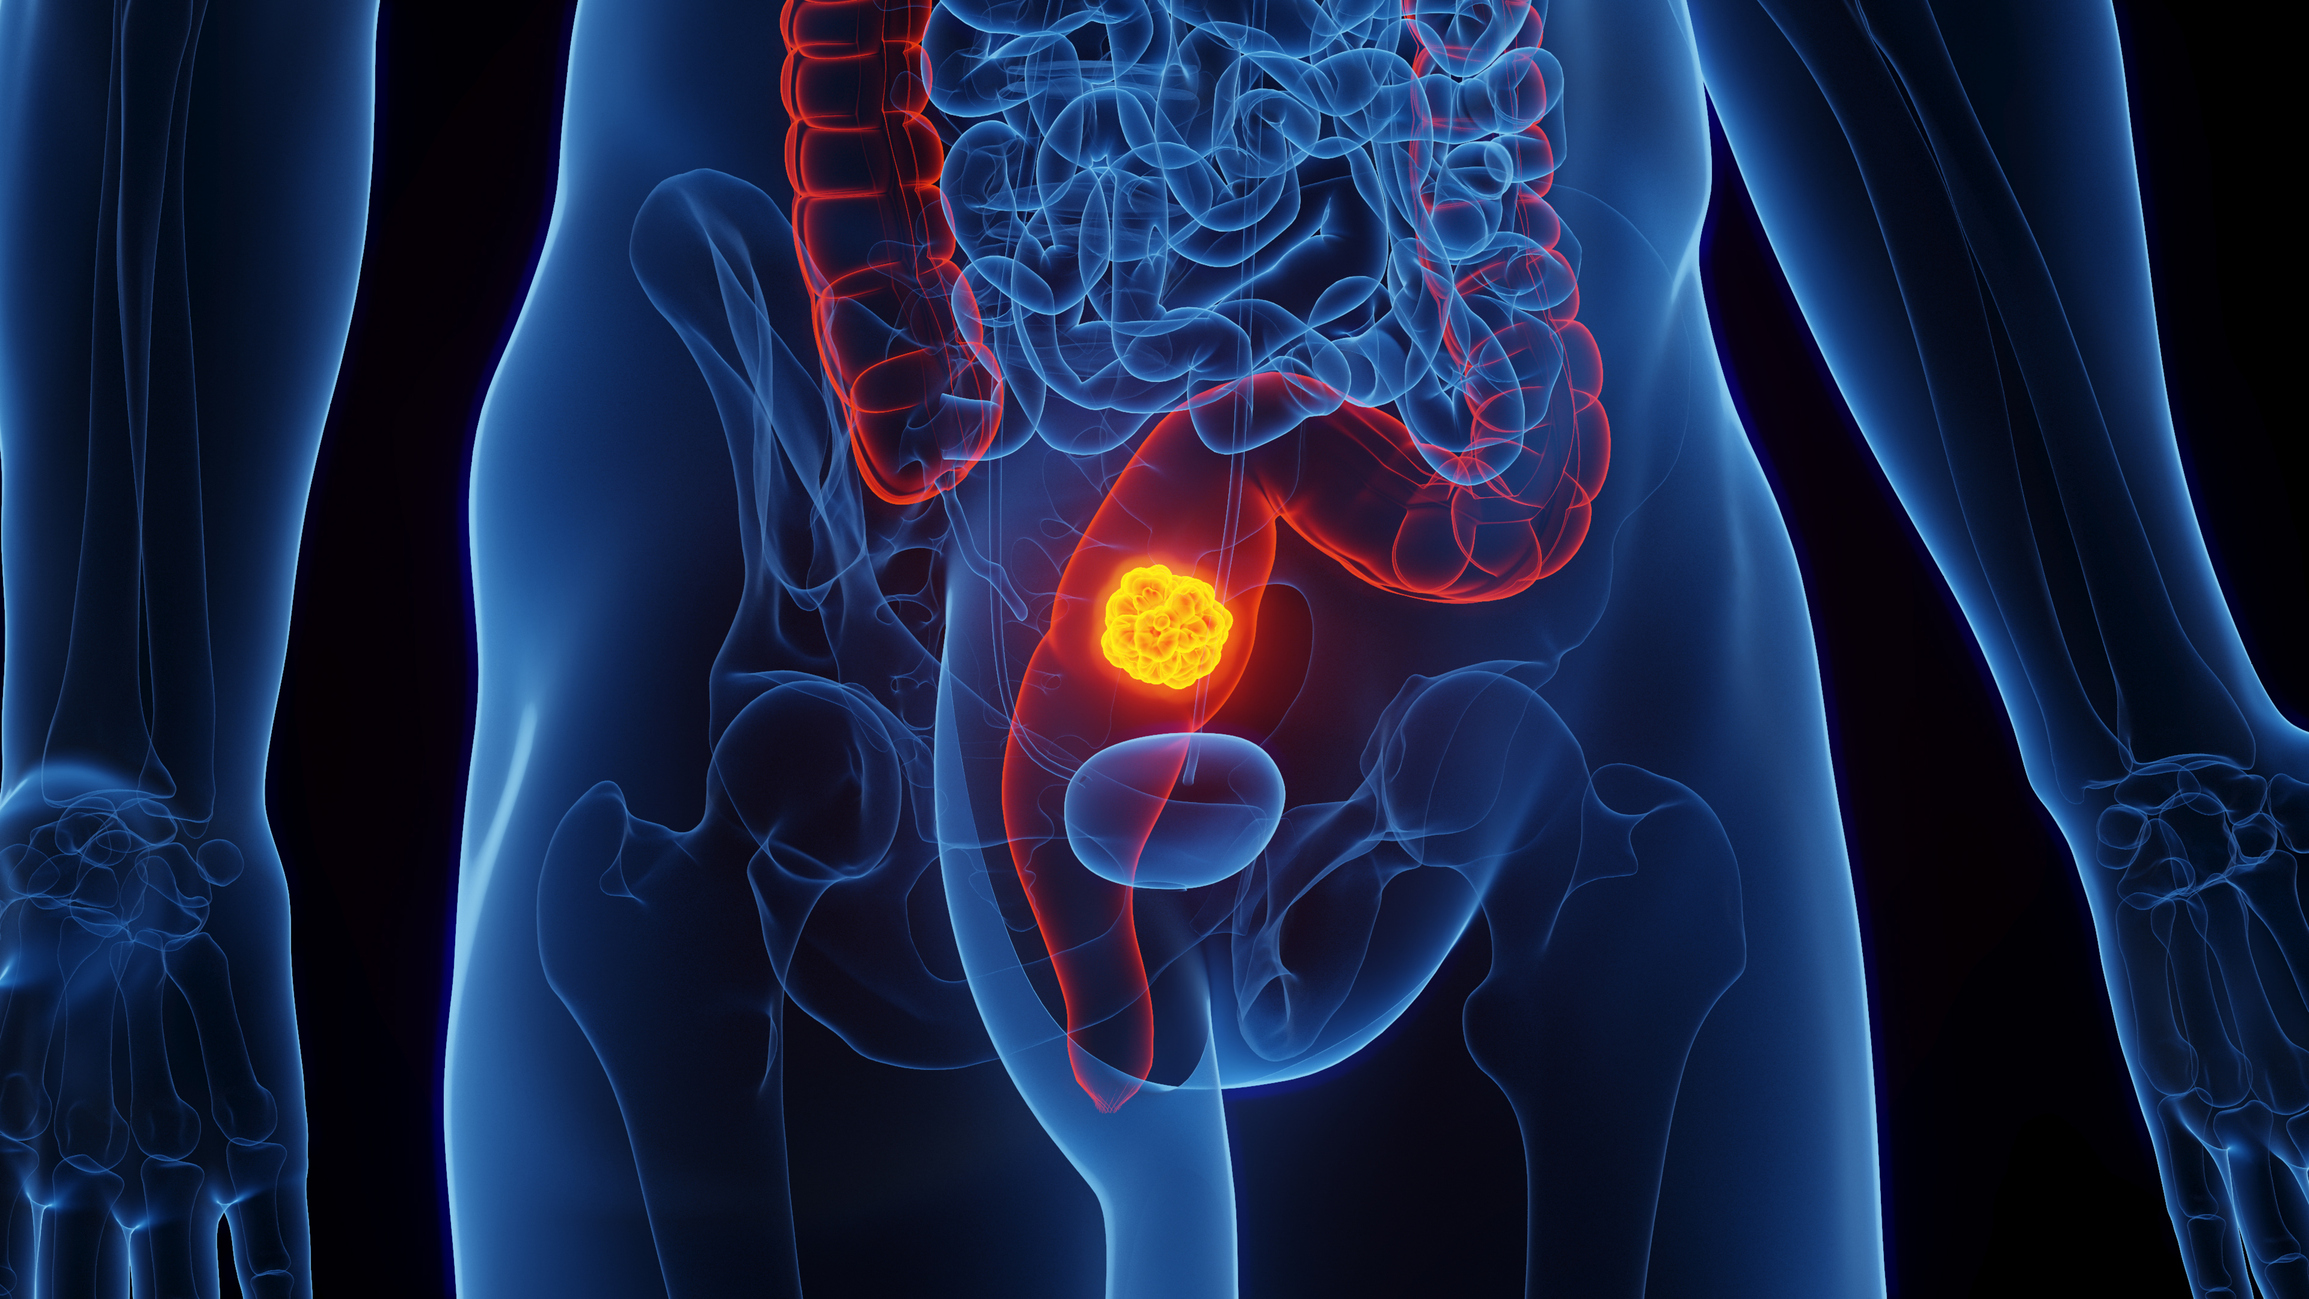
On Oct. 19, the U.S. Food and Drug Administration (FDA) approveddostarlimab (brand name: Jemperli) to treat a specific type of rectal cancer called microsatellite instability-high (MSI-H)/mismatch repair deficient cancer. This cancer is caused by the accumulation of certain genetic mutations that prevent rectal cells from repairing DNA damage and accounts for 5-10% of rectal cancers. In a study of 154 people with this type of rectal cancer who were treated with dostarlimab, 68% had a complete clinical response at one year, which meant doctors could not see evidence of tumors on imaging or other methods for tracking the tumors. In the study, which the drug's manufacturer, GSK, submitted to the FDA, people received nine infusions of the drug: once every three weeks for six months.
“Not only did they reach clinical complete response, but they maintained that for a year,” says Dr. Andrea Cercek, section head of colorectal cancer at Memorial Sloan Kettering Cancer Center and principal investigator of the study. (Some of the earliest patients have continued to remain tumor-free for even longer. ) “That really suggests that the response is durable and real.”
Dostarlimab is a checkpoint inhibitor, which means it releases the brakes that hold back the immune system from recognizing and attacking tumors. The drug allows immune cells to destroy cancer, making it a powerful weapon for seeking out cancer cells no matter where they spread or hide.
“We have completely leapfrogged over standard of care with a simple immunotherapy that melts the tumor away,” says Dr. Luis Diaz, head of solid tumor oncology at Memorial Sloan Kettering and one of the trial investigators.
The benefits of avoiding standard rectal-cancer treatment
Standard treatment for rectal cancer involves chemotherapy, radiation, and surgery to remove the rectum that requires patients to wear colostomy bags for the rest of their lives. The dostarlimab approval means more patients whose tumors have specific mutations could avoid those aggressive therapies altogether. “We have patients who would have lost the ability to bear children who have had children because this therapy replaced chemotherapy, radiation, and life-altering surgery in one swoop," Diaz says. "That’s a big deal.”
Kelly Spill is one of them. Diagnosed in 2020 when she was 29, shortly after having her first baby, Spill spent nearly nine months trying to figure out why she continued to have constipation and see bloody discharge in the toilet. Because she had recently given birth, doctors first attributed the symptoms to her pregnancy, and when they persisted after delivery, to internal hemorrhoids. It wasn’t until a doctor ordered a colonoscopy that they found a tumor.
“The doctor told me it was Stage III colorectal cancer, and that the treatment plan would include chemo, radiation, and surgery. And that I would never carry another baby again, and would most likely have a colostomy bag for the rest of my life,” says Spill. “It didn’t seem real until I heard the words that I was not going to carry another baby. I immediately stopped thinking about me, and started thinking about my husband and what it meant for my son. We had just started our lives together; we were supposed to have all these kids.”
Sascha Roth also faced devastating news when she was diagnosed with rectal cancer in 2019 after seeing blood in her stool. A resident of Washington, D.C., she had a friend with a similar diagnosis who had received chemotherapy, radiation, and surgery and recommended his surgeon at Memorial Sloan Kettering. Roth assumed she would follow the same strategy, but she learned that she had Stage III cancer and that she wasn’t a good candidate for surgery because the tumor was located so low in the rectum. Her tumor also had mutations that suggested it wouldn’t respond well to chemotherapy.
“It was a double whammy that threw me down,” she says. But the surgeon introduced her to Cercek, who was waiting to hear from the FDA about starting an immunotherapy trial for patients like Roth. “They told me I would be the first patient in the study, and there wasn’t scientific evidence that it would work.” Still, Roth wanted to try. She agreed to become Memorial Sloan Kettering’s first patient on the study, and then spent two months waiting for the FDA to greenlight the trial so she could begin receiving the drug. “I was calling Sloan Kettering incessantly to see if the FDA approved [the study],” she says. “The second the FDA gave its stamp of approval, Dr. Cercek’s team called me to New York to start the first round of treatment less than a week later.”
Not long after that, at Spill's first appointment at Memorial Sloan Kettering to discuss chemotherapy, she learned that the mutations on her tumor made her a good candidate for a study they had just begun. Only three patients had enrolled ahead of her (including Roth), so there was no data on whether it would actually treat her cancer. Spill, who was at the appointment with her mother, decided she had nothing to lose by joining the trial. “If it doesn’t go well, we could go back to option A,” Spill remembers her mother saying.
By her second infusion, Spill felt the tumor was shrinking because she no longer had major constipation. By the fourth infusion, scans showed the tumor had shrunk by 50%. The study originally called for patients to get chemotherapy, radiation, and surgery if needed after six months on dostarlimab. But a nurse pulled Spill’s mother aside after that appointment to tell her that the first three patients in the study did not need any additional treatments because their tumors had disappeared. Following Roth’s results, the study was revised to make chemotherapy, radiation, and surgery an option only if needed: if the tumors hadn’t gone away. It wasn’t a guarantee that Spill would have the same results as those first patients, but “it gave me hope, and all I could think about was maybe I could have another baby,” she says.
After all of her dostarlimab infusions, Spill, too, no longer had any tumor left and was declared cancer-free. Her doctors advised her to wait two years before trying to get pregnant again to ensure the cancer wouldn’t return. Once she was cleared, she got pregnant and gave birth to a girl in 2023, and later a boy in 2025. “I am now five years cancer-free, and last September got the boot from Memorial Sloan Kettering,” she says, meaning she no longer needs to follow up with her oncologists there. She now sees her primary care doctor for colonoscopies every two years.
“I see beauty in absolutely everything in life now,” Spill says.
What comes next for dostarlimab
Not only does the immunotherapy appear to work well in treating these rectal cancers, but it also comes with relatively few side effects. About 20% of those in the study reported fatigue, rash, diarrhea, and uncontrollable itching. Roth, who received her infusions during the COVID lockdown, drove from D.C. for her treatments and was able to make the roundtrip in one day. "It's just proof that you can really do the things you want to do. I didn't feel tired or sick after [the treatment], and there was never a time when I was at home recovering," she says. "I watched my mom and dad go through standard chemo and radiation and anticipated that would be what my treatment was like. It was nothing like that."
Cercek says the results point toward a potentially new model for managing some rectal cancers, which may include relying on immunotherapy like dostarlimab and monitoring patients more carefully before automatically turning to chemotherapy, radiation, or surgery. Some of the patients in the trial who were treated on dostarlimab underwent surgery after finishing their infusions if their doctors still felt there might be tumors remaining. Among them, despite the doctors’ suspicions, 80% did not turn out to have evidence of tumors in their specimens, says Cercek.
Dostarlimab is already approved to treat endometrial cancers with the same mutations and costs $10,000 to $12,000 per dose out of pocket, although GSK has a manufacturer's savings program to cover that cost for some patients.
“We still have a lot of learning about what complete clinical response means,” she says, and with immunotherapy, that might mean a more patient-centric, individualized approach that involves more time for the immune system to respond to the immunotherapy and become trained to attack the cancer. “If it looks like the tumor is responding, we need to give it more time with better techniques to determine whether or not the tumor is truly gone.”
Cercek and her team are studying the best ways to monitor how tumors respond to dostarlimab by looking at snippets of genetic information that tumors shed in the blood, or more advanced imaging to accurately capture changing tumor sizes. “We need to improve on those techniques but also to teach the oncology community that there is a very, very high chance that the tumor might disappear, even if it might not look like it at six months. We need to continue watching and waiting and giving it time.”
—Photo-Illustration by TIME (Source Image: Antenna/Getty Images)
Wait a second. You’ve been standing in line for 20 minutes, famished and desperate to order one of the viral bagels that keep selling out—or for six hours outside a concert venue, determined to claim a spot at the barricade to see your favorite band.
And then someone strolls up and slips in line ahead of you. Apparently, the rest of you have been standing around for the ambiance.
How much of a sin are line-cutters committing? “You are ripping the fabric of society apart,” says Nick Leighton, an etiquette expert and co-host of the podcast Were You Raised by Wolves? Queue-jumpers have to live with that, he adds. “But worse, we have to live with you.”
Here’s exactly how to handle this maddening situation—including when and how best to speak up.
When to speak up about someone cutting in line
If a stranger jumping ahead of you feels strangely personal, Richard C. Larson, a professor emeritus of data, systems, and society at MIT who has studied queuing, understands why. “We only have a finite number of minutes of life on Earth,” he says. The cutter’s implied message: “A minute of my life is worth more than a minute of yours.”
Before you decide whether to confront the offender, think about what speaking up would accomplish. Are you trying to reclaim your turn or get revenge? Sometimes, the impulse is “to sort of let them know you think they’re a jerk,” says Ryan Martin, a professor of psychology and dean of the College of Arts, Humanities and Social Sciences at the University of Wisconsin–Green Bay, known online as the Anger Professor because he studies strong emotions.
Martin would speak up to help someone recognize “that what they did wasn’t OK and that I wanted them to go to the back of the line,” he says. But he’d also consider: “What is going to allow me to have the kind of night I want to have?” If you spend the concert replaying a confrontation instead of singing your happy heart out, you’ve lost more than your place in line.
Leighton's gut check for situations like these is to ask yourself: Is this the hill you want to die on? “That’s always a good etiquette question,” he says.
Consider your safety, too. If the person seems hostile or you feel uneasy approaching them, you can ask staff for help or let the cut go. “Health and safety always trumps etiquette,” Leighton says.
What to say—if you do decide to say something
Marie Helweg-Larsen, a professor of psychology at Dickinson College who studies social norms, has explored what makes line-cutting so rage-inducing. For a 2008 study, she and a colleague surveyed U2 fans waiting for prime concert-floor spots, asking how they would react to hypothetical line-cutting scenarios.
Interestingly, fans reacted just as negatively to someone cutting behind them as ahead of them—even though their own place wasn’t affected. “You have to have people follow the rules,” she says, “or your investment into the line falls apart.” Helweg-Larsen’s co-author also heard fans invoke a higher authority when someone misbehaved: “Bono wouldn’t like that!”
You don’t need a rock star’s moral authority—or a grand speech—to point out where the line starts. Helweg-Larsen’s suggested opener: “Excuse me, but the line starts down there.” Aim for an “‘I’m just trying to be helpful’ kind of vibe,” she says.
That approach gives the person a chance to correct their mistake without having to defend their character. And you don’t have to believe it was an innocent oversight to deliver the message graciously. “Even if they’re doing it on purpose, you still need to use that tone,” Leighton says.
He’s been on the receiving end of a polite correction himself: At a deli, he once joined what he thought was the back of the line, only to discover he’d guessed wrong. He was happy for someone to point him in the right direction.
If you decide to speak up, do it promptly. “Your window of opportunity is short,” Leighton says. “As soon as it happens, that’s when you need to say something.” Waiting until you’ve spent five minutes glaring at the back of someone’s head won’t make the conversation any easier.
For a line that represents a serious investment of time, Martin suggests spelling that out: “Hey, I’m not sure you noticed, but there’s actually a really long line here, and people have been waiting all day.” You’ve identified the problem and given them an opening to say “Oops.”
Of course, some situations are murkier than a stranger breezing past the entire queue. Someone returning from a bathroom break is different from four friends arriving hours later to join the person who saved their places. Leighton is sympathetic to a water or restroom run. Holding spots all day for a last-minute entourage? “I don’t love that,” he says.
What to do if a line-cutter won’t move
Sometimes, your kind reminder won’t be met with the same level of helpfulness: They saw the line. They’re staying put. Now what?
If you feel comfortable continuing, Martin suggests a firmer follow-up: “I really think you should go back to the back of the line.” You’re making a direct request without adding an insult.
Larson advises skipping any confrontational nicknames or demands—like “What do you think you’re doing, bud?” You’re pointing someone toward the back of the line, not challenging them to a duel.
If the person still refuses to move, resist the urge to keep arguing. “We can’t control everybody,” Martin says. Continuing to push someone who’s already refused could lead to “a more significant confrontation.”
At a concert venue, amusement park, or other staffed location, you can ask an employee or security person to step in. “You can always appeal to a higher authority,” Leighton says. Whether they’ll enforce the rules is another question, but it’s an option worth trying when the cutting is particularly egregious.
If you decide to drop it, drop the parting shot, too. A sarcastic “Must be nice!” might feel irresistible, but Leighton advises against adding more rudeness to the encounter. “It will not achieve anything,” he says.
As Larson puts it, “A fight can ruin your whole day—or life.”

 Login